Quadfence Corp. · Sugar Land, Texas · Private alpha
A verdict, and the arithmetic behind it.
In December 2022 our founder bought a dental practice. Her accountant went through the books. Her broker handed her a page of census data: education levels, a gender split, a race breakdown.
Nobody could tell her how many dentists were already fighting over the same patients, or whether the neighbourhood turned over faster than she'd ever keep up with. She signed anyway. Most dentists do.
A corporate dental group has a marketing department — a strategist, a media buyer, an SEO lead, a content team, and an analyst whose job is to say which of the others is working. That costs hundreds of thousands a year and an independent practice cannot hire it. What it can hire is an agency: the same handful of people, shared with the practice down the road, accountable to none of its numbers.
We are building that department as software, for one practice at a time. AiRadics is the tool she needed and is now building. It tells a dentist whether a market can be won. Then, if they want it to, the platform goes and wins that market for them — and for nobody else in their territory.
Quadfence is the company underneath it. We build AI for decisions where being wrong is expensive, which means a recommendation is no use unless you can check it, see where it came from, and get the same answer twice. Dental is where we prove that. It is not where it ends.
178,000
US dental practices, mostly independent
under 5%
Largest share held by any single operator in US dentistry (IBISWorld)
4.3%
Of practices needed for a $1B outcome
The product, today
This is the screen a dentist opens in the morning.
The daily brief for our pilot practice. What the market looks like, what the gaps are costing, what the engine proposes to do about it, and what to do next — each play carrying the axiom it came from and the revenue it is worth.
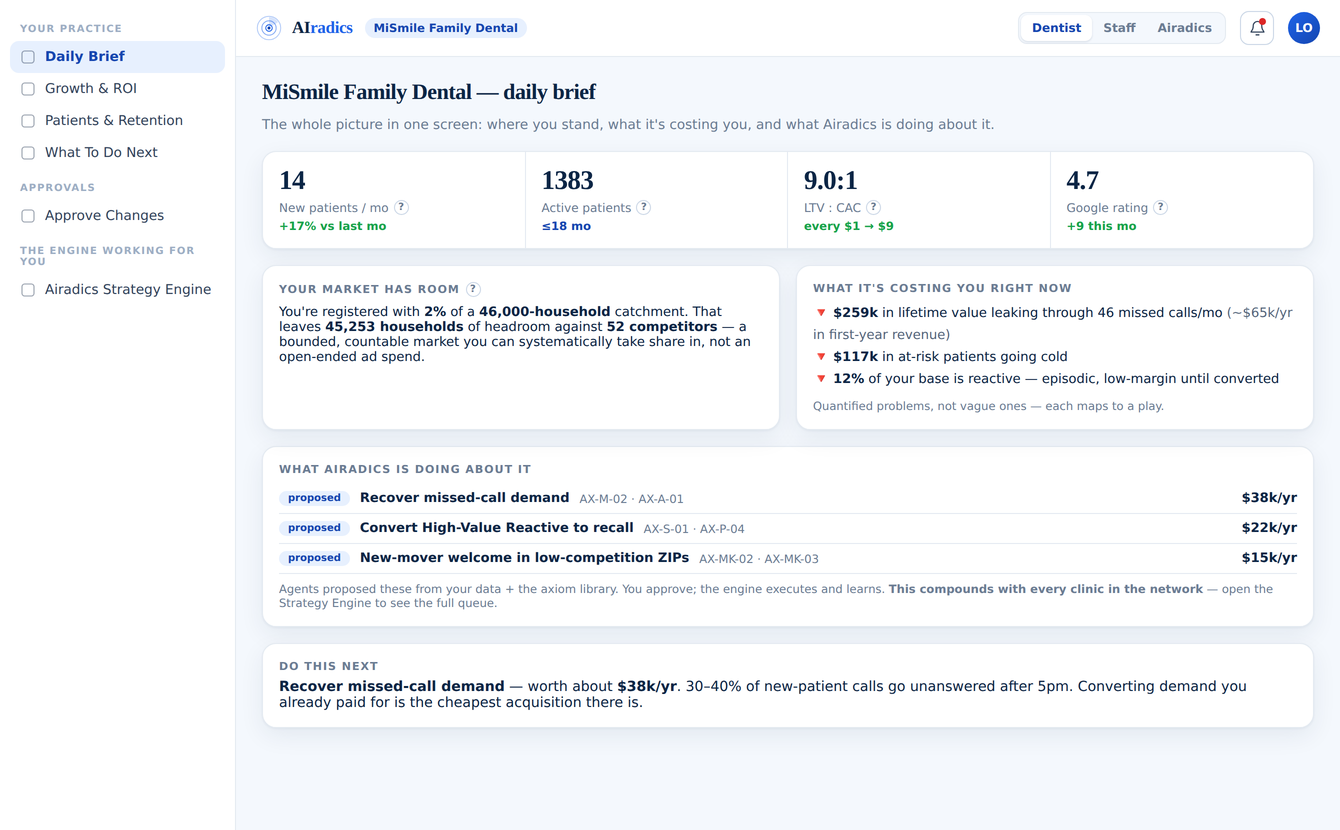
Four numbers at the top, because a dentist has eleven minutes between patients. The catchment stated as a bounded market rather than an open-ended ad budget. Losses quantified rather than described. Then the plays — each with an annual value and each carrying the axiom references it was derived from, so the practice can see which prior result produced the recommendation. Nothing executes until the dentist approves it.
Built on Google Cloud. Each practice runs in its own GCP project with its own BigQuery warehouse; channel data is ingested per practice and only aggregated, surrogate-keyed segments cross into the hub. The reasoning layer runs multiple models against the same question and requires agreement before anything acts.
What AiRadics is
An analyst and a production line, in one system.
Three jobs a marketing department does. Each is sold separately today, by different companies, to the same dentist — and none of them is accountable for the other two.
It reads the market
How many dentists per capita already compete for the same patients. How fast the households nearby turn over. What the payer mix on the ground actually is, and which clinical services the competition has left alone. A CPA can audit the books. None of this is in them.
It reads the money
Every channel reports in. The model works out what each one actually produces, what a patient costs through each of them, and where the next dollar earns most — then the budget moves. Not five numbers on a dashboard. An answer.
It makes the work
The website, the landing pages, the ads, the images, the video — all generated, and none of it live until it has cleared the governance gate: FTC rules, ADA guidance, the state dental board, and Google’s stricter standard for health content. No change orders, because producing an asset costs us a fraction of what it costs an agency to have a person make one.
An agency has people who can make the work but cannot honestly measure it. An analytics tool can measure but cannot make anything. In one system the analysis decides what to make — and making it is nearly free.
Why this team
One of us is the customer. The other has shipped governed AI inside a bank.
Dr. Soujanya Maddipati — Founder & CEO
DDS, Univ. of Colorado Denver · MPH, Univ. of Oklahoma
She has run Mi Smile Family Dental in North Houston since she bought it at the end of 2022. Medicaid, CHIP, Medicare Advantage, PPO. She still sees every patient herself. Then came three years of paying agencies she could not hold to a number, any of whom could have signed the practice a mile away the following week.
Dentists buy from dentists. That is not a marketing line, it is how the profession works, and you cannot hire it.
Chaitanya Maddipati — Co-founder & CTO
20 years, data & AI platforms in regulated industries
Most recently Senior Manager for Data and Cloud at Publicis Sapient, across UnitedHealth Group and TikTok. Before that, Executive Director and Principal Engineer at Wells Fargo over the bank’s customer data platform: forty engineers, a $15M portfolio, 900TB onto BigQuery, and the bank’s first application onto Google Cloud. Earlier, the data behind US credit-card acquisition at Capital One.
The hard part here is not generating marketing. It is generating it where almost nothing can be published unchecked and a regulator can ask why. Compliance runs before generation, not as a review afterwards.
Neither half works alone. An agency with better software still cannot get a dentist to trust it, and a dentist with a good idea cannot ship a governed multi-model engine.
Pilot & MVP development customer
We build against a live practice before we sell to a second one.
Quadfence does not build AiRadics against a specification and then look for someone to sell it to. Every module is built, run and optimised inside a working general practice first — the channels, the content generation, the template repository and the governance gate all shipped against real data, a real payer mix and a real patient book before they are offered to anyone else.
That practice is Mi Smile Family Dental in North Houston, our pilot and MVP development customer. Dr. Maddipati bought it in December 2022 and still operates it, so it is a related-party engagement and we say so plainly rather than leave it to be found.
We chose it because it is the hard case. Four payer classes in one book — Medicaid, CHIP, Medicare Advantage and commercial PPO. A mixed catchment across income bands and language groups. The full procedure set a general dentist bills, plus patient financing. Most single-clinic pilots teach you one path. This one exercises nearly all of them at once, which is why what it produces generalises instead of having to be relearned.
What we have to show before we sell to anyone else: that the engine moves the numbers here, and that a second practice can be stood up from the same blueprint in a day. Twenty shallow clinics would produce twenty thin datasets. One clinic exercising every payer class produces an ontology the twenty-first can actually use.
The market
A $1B outcome needs 4.3% of one fragmented vertical.
Each number below is a count of practices multiplied by what one pays us in a year. We haven't borrowed anything from a bigger adjacent market to make it look larger.
$2.88Bgross market
178,000 US practices at an indicative $16,200 annual contract value. Recurring fee only — media runs on the practice’s own accounts and is excluded.
$1.87Bserviceable
Independent practices only. We assume 65% remain independent, and affiliation is reported at 13–16% today. We have deliberately left small and mid-size DSOs out of this number even though they are buyers too, which means consolidation is less of a risk here than the figure implies.
4.3%share required
7,716 practices at the same indicative figure is $125M ARR, which is roughly a $1B company at an 8× multiple. We would be the largest player in this niche and still hold four percent of it.
We don't have to win this market, only a slice of it. The three largest dental marketing agencies we can put a number to serve roughly 9,100 practices between them, which is 5.1% of the market. The leader has 4.2% after twenty-three years and private-equity backing. Sizes and sources are set out below. The engine itself doesn't care that the customer is a dentist, which is why small medical practices are the obvious second move. Same shape of problem, different vocabulary.
The round
We are not raising to find out whether this works. We are raising to go faster.
The goal is a marketing department that costs what an agency costs and belongs to one practice. We are not there yet. What stands between here and there is an ontology and a governed engine, built against a real practice with a real payer mix, and that is in progress. What money buys is the part that is purely capacity: finishing the product, and putting clinics onto it.
A new practice is provisioned from the same blueprint every time rather than built — which is what makes a one-day onboarding possible and an agent-led sale viable. Pricing sits in line with what a practice already pays an agency for two channels and nothing else, and includes considerably more.
Where we are, precisely: in private alpha, running inside one practice — our pilot and MVP development customer, which our founder owns. That is a development engagement and not a customer base, and we are not going to present it as one. What exists is a working system, a practice whose numbers it is being measured against, and the ontology it is producing — not a slide, and not twenty shallow trials.
Get in touch
Request early access, or ask for the deck.
We are in private alpha and taking a small number of Texas practices into the first cohort. Investors: the deck and the operating model are available on request.